
Every living-donor kidney transplant involves two patients: one whose life depends on receiving a healthy organ, and another who undergoes surgery despite being well. That places a particular responsibility on the transplant team. A good outcome is not only a functioning kidney. It is also a donor who recovers safely and returns to life with as little disruption as possible.
The Growing Need For Safer Living-Donor Kidney Transplants
This balance matters greatly in India, where the number of people who need a kidney transplant is far higher than the organs available, and living donors remain central to meeting that need. While deceased donation must grow, we must also keep asking how living donation can be made safer and less physically demanding.
For the recipient, transplantation comes after years of living with kidney disease. Medicines, dietary restrictions, hospital visits and dialysis may have shaped everyday life. A transplant can offer freedom from much of this routine, but recovery from the surgery remains an important part of the journey.
ALSO READ | Doc Talk | Wounds Taking Too Long To Heal? 5 Health Factors That Could Be Slowing Your Recovery
How Robotic-Assisted Surgery Can Support Recovery
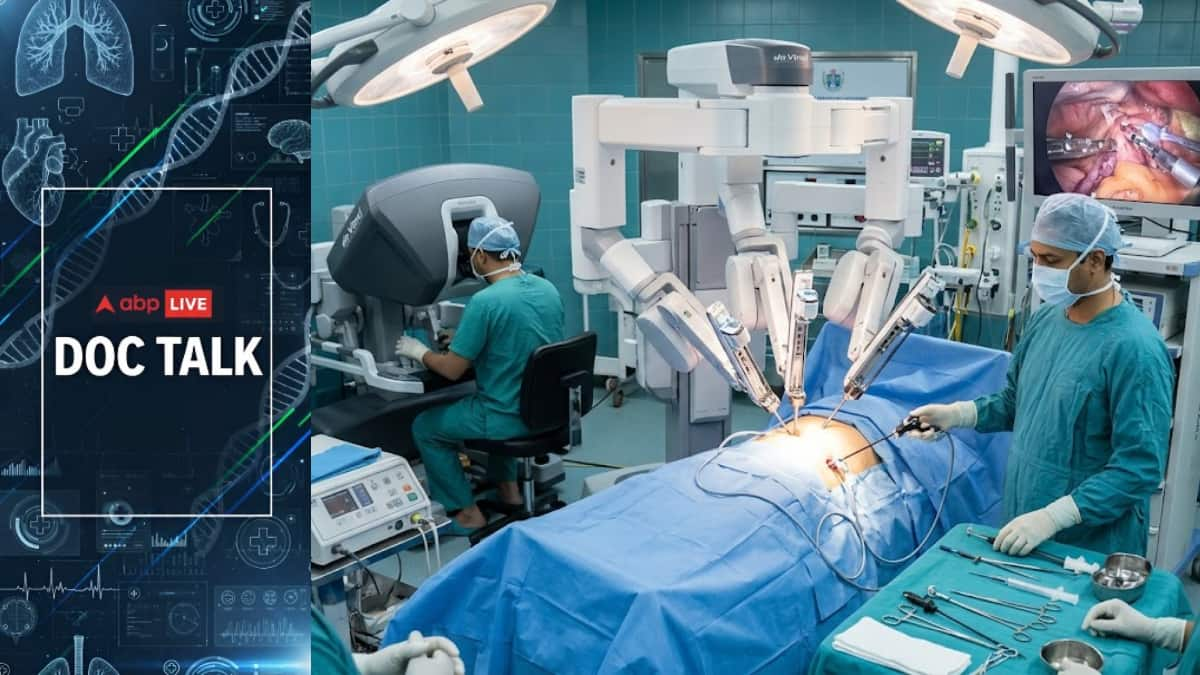
In my experience with the da Vinci surgical system, robotic-assisted surgery can make recovery less physically demanding for patients. Three-dimensional visualisation, articulated instruments and tremor filtration allow surgeons to perform precise dissection and suturing in confined spaces. By enabling the procedure to be performed through smaller incisions with less disruption to surrounding tissue, the approach may help reduce wound-related problems and support early recovery.
This can be particularly relevant when transplantation is technically more demanding. Obesity, previous abdominal surgery or altered anatomy may increase operative complexity and the risk of wound complications. Such circumstances make careful assessment and individualised surgical planning especially important. Two patients we treated recently are good examples.
The first was a 53-year-old man with chronic kidney disease who had previously had a kidney removed. His niece donated a kidney, and he had stable early graft function. The second was a 42-year-old woman with autosomal dominant polycystic kidney disease. Her mother donated, allowing her to receive a transplant before dialysis became necessary. She, too, recovered steadily.
ALSO READ | Doc Talk | Diabetes Warning Signs: 5 Foot Symptoms You Should Never Ignore
Why Individualised Surgical Planning Matters
The cases differed in their anatomy, disease course and timing. What they had in common was the need for a surgical plan shaped around the individual patient. The decision to use a robotic approach cannot begin with the technology. It must begin with the recipient’s condition, the donor organ, the surgeon’s assessment and the experience of the transplant team.
Prioritising Donor Safety And Recovery
The donor’s experience requires equal consideration. A living donor accepts the risks and disruption of surgery entirely for another person’s benefit. We therefore have an obligation to make donation as safe and physically manageable as possible.
Robotic-assisted donor nephrectomy offers a minimally invasive way to remove the kidney, with the potential for less postoperative discomfort and an earlier return to normal activity. It will not, by itself, increase organ donation. Families make these decisions based on medical, emotional, social, and ethical considerations. But if surgery becomes less daunting for the donor, it can remove one source of anxiety from an already difficult decision.
Building The Right Infrastructure For Robotic Transplantation
The future of robotic transplantation will depend on how responsibly it is developed. A robotic system alone does not create a transplant programme. Hospitals need trained surgeons, anaesthetists, nephrologists, operating-room teams and critical-care specialists working within established protocols. They also need systems for donor evaluation, patient selection, postoperative care and long-term follow-up.
Training is especially important because transplantation leaves little room for inconsistency. Surgeons must have experience in both transplant and robotic surgery, supported by structured mentorship. The objective is not to make every transplant robotic. It is to recognise where the approach can offer genuine clinical value and where conventional surgery remains the better choice.
Measuring Outcomes Beyond Technology
Data can also help hospitals benchmark performance, strengthen training and identify areas for improvement. But decisions in transplantation will continue to depend on factors that cannot be reduced to an algorithm: the recipient’s health, the donor’s safety, organ quality, anatomy and the likely long-term outcome.
India must therefore build evidence alongside capability. Robotic transplantation should be judged by measures that matter to donors and recipients: surgical complications, graft function, recovery, quality of life, long-term outcomes and value across the full course of care.
Disclaimer: The information provided in the article is shared by experts and is intended for general informational purposes only. It is not a substitute for professional medical advice, diagnosis, or treatment. Always seek the advice of your physician or other qualified healthcare provider with any questions you may have regarding a medical condition.